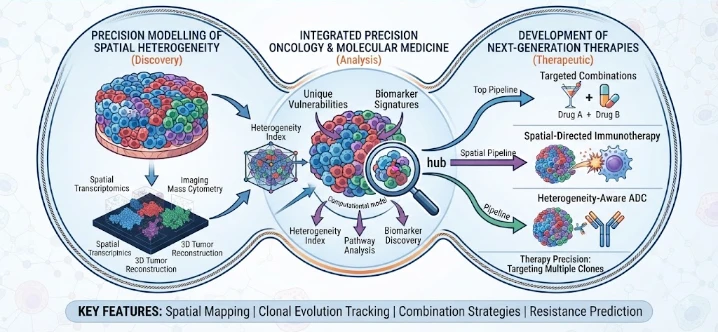
This article frames tumor spatial heterogeneity as a therapeutic target in precision oncology. Tumors contain distinct clones, immune niches, stromal barriers, vascular regions, metabolic states, and drug-sensitive or drug-resistant microenvironments that cannot be captured by a single biopsy or bulk average. The article links clone location, cell–cell interaction, vascular access, immune state, pathway activity, local drug exposure, and regional treatment response using spatial transcriptomics, multiplex imaging, imaging mass cytometry, multiregion sequencing, digital pathology, and functional perturbation. Spatial statistics, graph models, agent-based simulation, radiogenomics, Bayesian mapping, and multiscale PK–PD are proposed for integrating these measurements. Longitudinal spatial profiling, residual-disease mapping, post-treatment biopsies, and resistant-clone sequencing help identify protected regions that can drive relapse. The framework also considers tissue penetration, diffusion distance, interstitial pressure, target engagement, toxicity, sampling quality, assay reproducibility, and clinical feasibility of biopsies or imaging. The central message is that spatial information becomes actionable when it predicts where treatment will succeed or fail and guides therapy toward otherwise protected tumor regions.
Tumors are not a single mass of cancer cells but instead are spatial ecosystems. The spatial heterogeneity in precision oncology has gone beyond the simple discovery of hits as we realize that only a single biopsy or bulk averages can miss clonal diversity, immune niches, stromal barriers, regional metabolism and drug-sensitive microenvironments. The more important question has to do with whether a spatial model that characterizes therapeutically relevant regions and indicates treatment pressure zones that will be effective (or ineffective) in realistic biology and development scenarios will remain robust under realistic conditions. This change is from a ranking activity to a discovery program based on exposure, cause and repeatability. As the arrays of molecular structures available for spatial precision oncology grow, the ability to correlate structure with experiments to discover why a candidate works, where it doesn't, and which constraints are most important is becoming more critical by the publication deadline.
New technologies such as spatial transcriptomics, multiplex imaging, digital pathology, multiregion sequencing and radiology show the diversity of genotype, phenotype and microenvironment within a tumour. Past experience and recent development demonstrates that as biological complexity (neurons, etc.) increases, it is hard to find a nice laboratory signal that remains as is. A helpful research methodology is then to maintain a fairly strong activity signal while adding a more realistic context to which the signal must be effective.
Mechanistic depth begins by linking together the location of the clone, cell-cell interaction, vascular access, immune state, pathway activity and the local drug response. This structure can be concealed by simple endpoint assays as similar readouts can occur from different causal pathways. However, a richer picture is provided by the separation of the direct action from downstream adaptation, nonspecific stress or delivery failure, which is provided by the spatial transcriptome, multiplex immunofluorescence, imaging mass cytometry, multiregion sequencing, digital pathology, and functional perturbation. These measurements allow for the creation of an attractive response that can be tested as a chain of chemistry, biological state and functional outcome.
Design variables should also be considered in an interactive manner, rather than as separate factors. These factors interact with each other: a better performance in one of these dimensions may result in a penalty in another. Therefore it is more practical to try to optimize trade-offs, rather than a single maximum. Multi-parameter profiles are particularly informative when potency, selectivity, stability, tissue exposure and manufacturability all impact the translational value.
When uncertainty can be seen, the addition of computational leverage provided by spatial statistics, graph models, agent-based simulation, radiogenomics, Bayesian mapping and multiscale PK-PD allows prediction to be useful. When assessing a novel scaffold or material, or an underrepresented patient state, models trained on existing chemical or biological regions may be unreliable. Fragile predictions are exposed due to calibration, prospective testing, domain-of-applicability checks and disagreement across model families before costly experiments are conducted.
Orthogonal validation is used as a tool for experimental design. Multiregion sampling and matched imaging, longitudinal biopsies, ex vivo perturbation, independent cohorts and treatment response mapping address various components of the causal question and minimize reliance on any individual assay technology. The more agreement from chemistry to imaging to omics to genetics to functional biology, the more mechanistic of an argument—than is repeatedly measuring the same endpoint. Discussed also, however, is disagreement as an informative element, for different outcomes can be indicators of hidden exposure thresholds, assay artifacts, compensatory pathways, or context-dependent pharmacology.
Biological diversity complicates matters a bit more. The nominal treatment may not change target abundance, barrier properties, metabolism, immune tone or pathway dependence, even if target abundance or barrier properties vary between the primary and metastatic site, or with treatment history, target purity, tissue architecture, sampling depth, disease stage, etc. Average responses thus may not reflect subgroups that may have different exposure-response relationships. Biological variation is a component of design and not just an afterthought to explain inconsistent results using stratified analysis, representative model panels and explicit covariate testing.
Early focus on resistance and adaptation is warranted as there may be protected clones or microenvironments that are the source of relapse, which may be eliminated by therapy. Longitudinal spatial profiling, residual-disease mapping, resistant clone sequencing, post-treatment biopsies and evolutionary modeling can be used to identify whether or not activity is present under evolutionary or compensatory pressures. A candidate that is not as potent, but has limited escape pathways may have more long term value than a more fragile high potency candidate. Resistance-aware development also can hone mechanism as recurrent escapes often will point to the proteins, pathways or exposure processes with the most causal influence.
Molecular promise to reachable biology through delivery and pharmacokinetics. The active form will reach its target only at a concentration and duration suitable for its proposed mechanism if: vascular delivery, the distance of diffusion, the interstitial pressure, binding, metabolism, regional uptake, and intracellular target engagement are suitable. This relationship cannot be adequately conveyed in a nominal dose format as the absorption, distribution, binding, transformation, clearance and local barriers change the effective exposure. Mechanistic exposure assessments should, therefore, be placed along with efficacy data from the earliest development stages.
Mechanism is a powerful tool that can enhance the safety assessment. Normal-tissue exposure, immune-related toxicity, off-target tissue engagement, organ function and dose-limiting effects can help to distinguish target-linked pharmacology from general cellular toxicity, immune activation, reactive chemistry and formulation-related toxicity. Comparative testing in diseased and healthy systems determines the therapeutic activity from the undesirable one. The latter is because this method leaves a desirable efficacy signal to develop a program without the same effect gradually closing the exposure window in the program.
Another scientific variable is manufacturing, not a downstream logistics issue. Product quality, biological activity, and exposure can change due to assay reproducibility, tissue processing, imaging calibration, sequencing workflow, computational pipelines, and even exposure to the same nominal composition, for example, during tissue processing. In quality-by-design thinking, the source attributes and process parameters of the material are not only correlated with each other, but also with measurable performance, rather than end-stage specification testing alone. Industry success that's independent of raw material variation, larger equipment, storage and transport, and independent production runs makes for more believable scalability.
There also needs to be realistic models of clinical use to aid translation. Treatment timing, dose frequency, route, necessary imaging, diagnostic requirements, and appropriate complexity influence treatment timing.Treatment timing is influenced by biopsy feasibility, turnaround time, metastatic accessibility, treatment urgency, imaging availability and biopsy interpretability for tumor boards. A technically beautiful platform, which is not useful in the setting where treatment is required, because its administration requirements, storage conditions or monitoring requirements are too high, or because of the cost, is not of practical value. Thus, the judicious choice of development decisions can be optimized in early stage commitments when it is easier to change than when we are near the end of the process.
Data integration is the link between these layers. Causal models can be used to coordinate data on coordinates, cell states, genomic alterations, transcripts, proteins, pathology, imaging, drug exposure, and outcomes, instead of simply having them as independent assay outputs. Iterative learning is reproducible thanks to traceable metadata, versioned models, standardized controls and prospective decision rules. The end result is a development record that reveals not only which one candidate came out on top, but what the assumptions were on which that candidate was made, and what the uncertainties were that were left unanswered.
Spatial models require a predictive accuracy, coverage of clones, sampling robustness, localization of the treatment response, calibration, reproducibility and added-value over the traditional biomarkers at the regional level. The higher the quality of the decision, the more parameters that are used to measure success are durable, reproducible, exposure margin, biological breadth, and manufacturing robustness as well as potency. These metrics incentivize candidates to optimize for a specific assay, instead of a general one, and make it more likely that a candidate will be retained if they are found to be credible by an independent assay. The rationale of a less dramatic outcome being the development option is also made clear by a transparent scorecard.
Also, a strong program specifies a constructive way of failure. Negative results, single-region over-confidence, batch driven spatial patterns, low tumor purity, inaccessible metastases and non-reproducible segmentation and descriptive maps without treatment relevance outline the boundaries of the mechanism and minimise repeated investment in weak hypotheses. These factors can lead to a lack of synthesis, to a lack of target engagement, to unstable exposure, to the emergence of resistance, or to the loss of effect in subgroups.The absence of synthesis, a lack of target engagement, unstable exposure, emergence of resistance or lack of effect in subgroups can all give a future model a more realistic view of the search space. Discovery is quicker if the negative experiments teach as much as the positive ones.
When spatial data shows space that can be acted upon and space that can be connected and space that is blocked from contact, then spatial heterogeneity becomes a therapeutic target. The core benefit of the central advantage is to provide explanations that link together rather than, or in addition to, isolated performance claims, covering the mechanism, the exposure, biological diversity, safety and production. That structure allows for optimum candidate selection as each significant development claim has a test. Progress is more about a series of experiments that links together in a convincing way, rather than dazzling individual experiments, as complexity increases from laboratory systems to actual clinical situations.
CITE THIS ARTICLE
Kabir, M. H. (2025). Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies. https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d
M. H. Kabir, “Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies,” 2025. [Online]. Available: https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d
Kabir, M. H. (2025) ‘Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies’. Available at: https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d
Kabir, Md. Humayan. “Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies.” 2025, https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d.
Md. Humayan Kabir. “Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies.” (2025). https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d.
Kabir MH. Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies. 2025. https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d
@misc{article_22268912f81b5d5bae3baf88d1245d9d,
  title = {Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies},
  author = {Md. Humayan Kabir},
  year = {2025},
  url = {https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d},
}
TY  - GEN
AU  - Md. Humayan Kabir
TI  - Spatial Heterogeneity as a Therapeutic Target: Precision Modelling of Precision Oncology, Molecular Medicine, Biomarkers and Next-Generation Therapies
PY  - 2025-11-30
UR  - https://researchbykabir.com/article/22268912-f81b-5d5b-ae3b-af88d1245d9d
ER  -
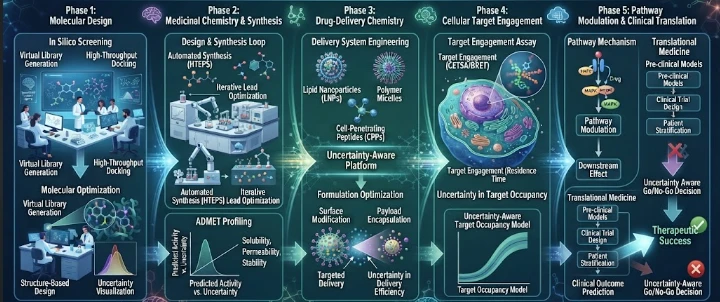
This article describes an uncertainty-aware platform for moving from predicted molecular binding to validated cellular target engagement in medicinal chemistry and drug-delivery research. Docking and machine-learning predictions can rapidly prioritize compounds, but they do not establish that a molecule reaches, occupies, and functionally modulates a target inside relevant cells. The article therefore separates predicted affinity from free intracellular concentration, subcellular localization, t
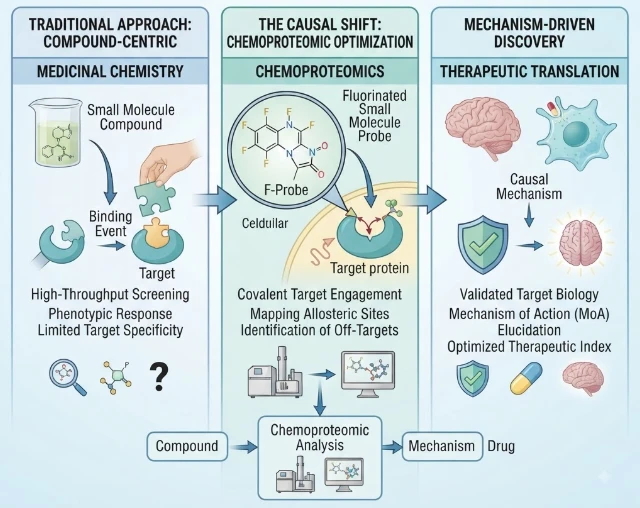
This article explores fluorinated medicinal chemistry through causal chemoproteomics, emphasizing that fluorine substitution can alter far more than potency. A single positional change can modify conformation, pKa, lipophilicity, metabolic stability, target interactions, intracellular exposure, and off-target biology. The article therefore tests whether fluorinated analogues change cellular phenotype through intended target engagement rather than hidden polypharmacology. Matched molecular pairs
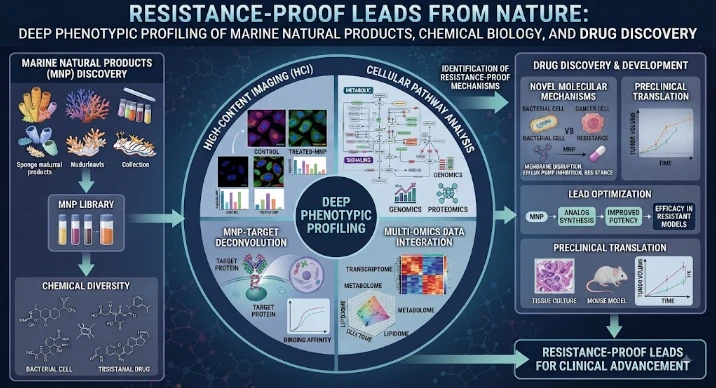
This article presents resistance-aware marine natural-product discovery as a mechanistic process rather than a search for isolated high-potency hits. It explains how activity from marine extracts or fractions can disappear during purification or fail under resistance pressure, making deep phenotypic profiling essential. Morphology, viability kinetics, organelle function, transcriptional state, metabolism, and recovery after washout are combined to connect phenotype with mechanism. The article em